
Most of what goes wrong happens between appointments.
Diabetes, heart failure, COPD, kidney disease, hypertension, dementia. None of these break on schedule. They drift. Then a small drift becomes an ambulance.
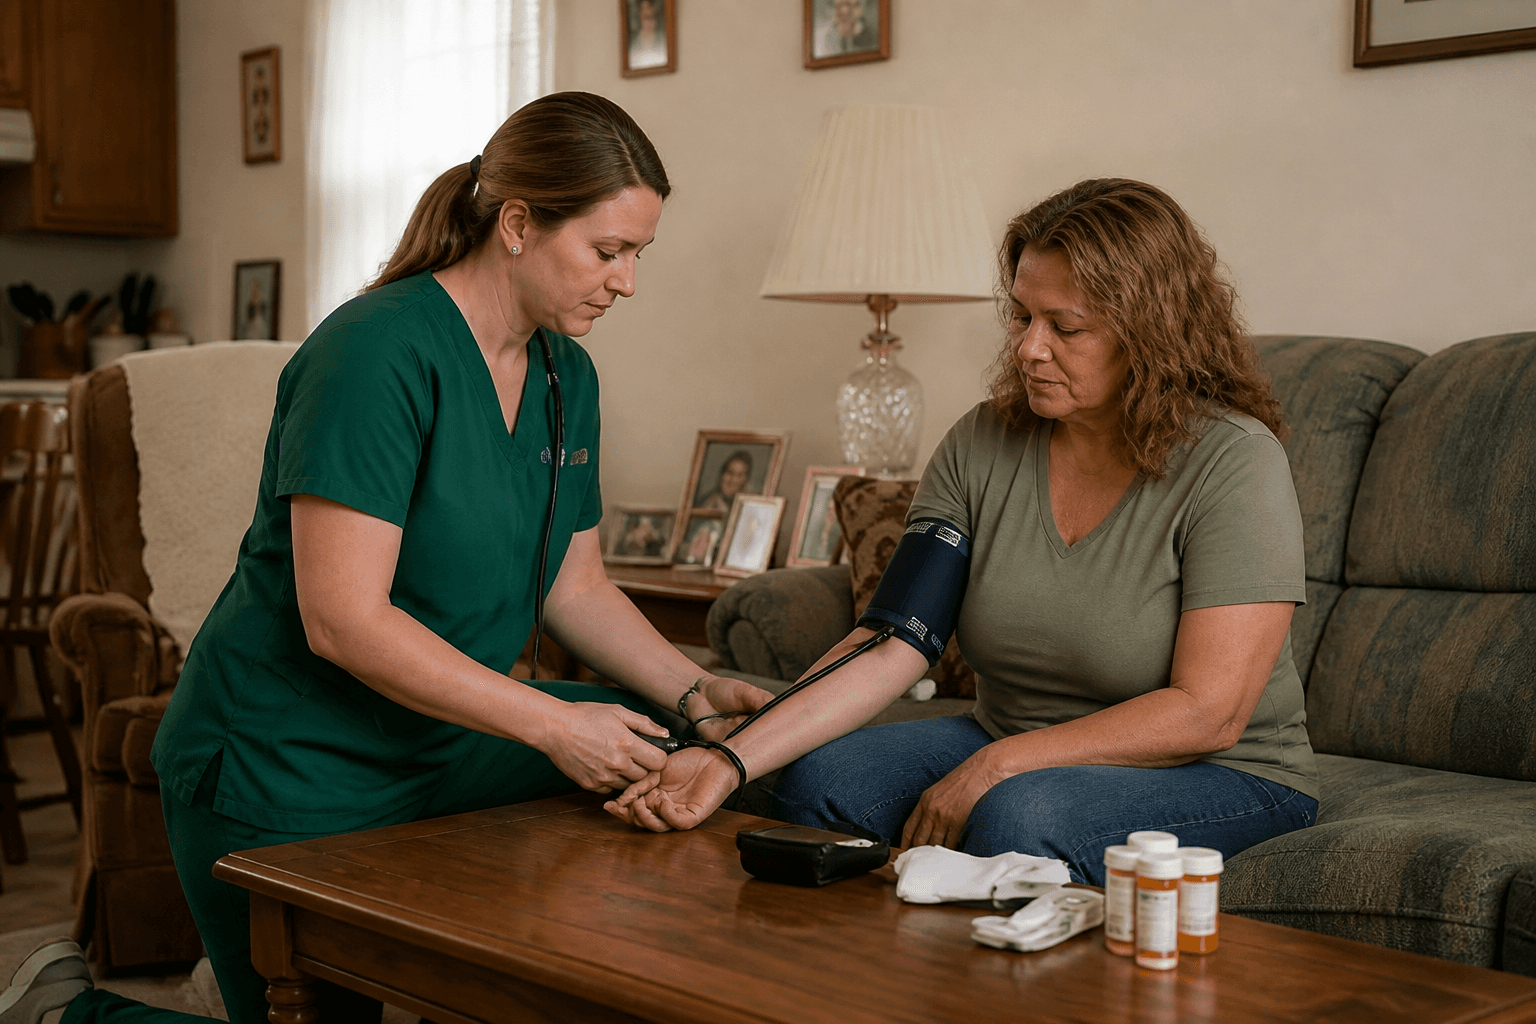
Quarterly office visits catch drift late by design. We are in the house often enough to catch it early, and close enough to adjust without waiting for the next opening.
How that works in practice.
We visit on the rhythm the condition needs.
Monthly for most patients. Weekly after a bad stretch, until things settle again.
Medication gets reviewed every time.
Older patients on eight-plus medications is common, and interactions cause more crises than the underlying disease.
We watch the numbers between visits.
Weights for heart failure, glucose logs for diabetes. Reviewed, not just collected.
Families get told what to watch for. Specifically.
"Call us if she gains three pounds in two days" beats "call if anything changes."
Conditions we manage most.
- Diabetes
- Heart failure
- COPD and chronic respiratory disease
- Hypertension
- Chronic kidney disease
- Dementia and cognitive decline
Common questions
How the care works
The ones that come up on nearly every first call.
Still unsure? Call (872) 260-0204 and describe an average morning.
Get started
The next appointment doesn't have to be a production.
Tell us what is going on and we will tell you honestly whether we are the right fit. If we are not, we will say so.